Obstruction to LV inflow at the mitral valve — almost always rheumatic; opening snap with diastolic rumble.
Also known as: MS, mitral stenosis, rheumatic mitral disease
Overview
Narrowing of the mitral valve orifice that obstructs diastolic flow from left atrium to left ventricle. Worldwide, almost exclusively rheumatic; degenerative calcific MS is increasingly recognized in older Western patients.
Epidemiology
Most common cause of valvular disease in regions with endemic rheumatic fever. Female predominance ~3:1. Symptoms typically develop 10-30 years after the inciting streptococcal infection.
Try two board-style Mitral Stenosis questions
Real questions from the FirstPassPA bank, with the full explanation. Pick an answer — no signup, no email.
Question 1CardiovascularMedium
A 65-year-old woman with a history of rheumatic fever in childhood reports several months of exertional dyspnea and palpitations. On auscultation there is a low-pitched diastolic rumbling murmur best heard at the apex, preceded by an opening snap and loudest in the left lateral decubitus position. A chest radiograph shows left atrial enlargement with straightening of the left heart border. Which of the following is the most likely diagnosis?
ATricuspid stenosis
BAortic stenosis
CMitral regurgitation
DMitral stenosis
EAortic regurgitation
Reveal answer & full explanation
Correct answer: D — Mitral stenosis
ATricuspid stenosis
BAortic stenosis
CMitral regurgitation
DMitral stenosis✓
EAortic regurgitation
Why Mitral stenosis is correct
A low-pitched diastolic rumble at the apex with an opening snap, accentuated in the left lateral decubitus position, is the classic auscultatory signature of mitral stenosis.
The opening snap reflects the abrupt halt of doming, thickened (rheumatic) mitral leaflets; a shorter snap-to-S2 interval correlates with more severe disease.
Obstruction at the mitral valve raises left atrial pressure, producing the left atrial enlargement on chest radiograph and explaining the dyspnea and palpitations (atrial fibrillation risk). Rheumatic heart disease is the leading cause, fitting her childhood history.
Why the others are wrong
Aortic stenosis — a systolic ejection murmur at the right upper sternal border radiating to the carotids, not a diastolic apical rumble. Trap: buzzword-matching 'stenosis' without timing the murmur.
Mitral regurgitation — a holosystolic murmur at the apex radiating to the axilla; it occurs in systole and has no opening snap. Trap: right valve, wrong part of the cardiac cycle.
Aortic regurgitation — an early diastolic decrescendo murmur at the left sternal border with a wide pulse pressure, not an apical rumble with an opening snap. Trap: pairing 'diastolic murmur' with the wrong valve.
Tricuspid stenosis — usually rheumatic as well and also produces a diastolic rumble, but it is heard best at the left lower sternal border, grows louder with inspiration, and enlarges the right atrium, rather than producing an apical rumble with left atrial enlargement; when rheumatic, it nearly always accompanies mitral valve disease. Trap: right murmur timing, wrong valve.
Question 2CardiovascularMedium
A 70-year-old woman with known rheumatic mitral stenosis presents with acute dyspnea. An echocardiogram 3 months ago showed a mitral valve area of 1.0 cm2 and a left ventricular ejection fraction of 60%. She is found to be in new atrial fibrillation at a ventricular rate of 145 beats per minute, with bibasilar crackles, an oxygen saturation of 88% on room air, and frothy sputum consistent with acute pulmonary edema. Her blood pressure is 118/76 mm Hg. She is alert with warm extremities, and her oxygen saturation improves to 93% on supplemental oxygen. Which of the following is the most appropriate initial intervention to relieve her pulmonary edema?
AIntravenous metoprolol
BSurgical mitral valve replacement
CPercutaneous mitral balloon commissurotomy
DIntravenous adenosine
EIntravenous amiodarone
Reveal answer & full explanation
Correct answer: A — Intravenous metoprolol
AIntravenous metoprolol✓
BSurgical mitral valve replacement
CPercutaneous mitral balloon commissurotomy
DIntravenous adenosine
EIntravenous amiodarone
Why Intravenous metoprolol is correct
In mitral stenosis, left atrial emptying depends on adequate diastolic filling time; tachycardia shortens diastole, raises left atrial pressure, and rapidly drives pulmonary edema.
New atrial fibrillation at 145/min is what tipped her severe stenosis (mitral valve area 1.0 cm2) into pulmonary edema. IV metoprolol slows AV-nodal conduction, lengthens diastolic filling time, and lowers left atrial and pulmonary venous pressure. It treats the cause of the edema, which is why it is the best answer to what is asked.
IV beta blockers are recommended for acute rate control of AF with a rapid ventricular response in hemodynamically stable patients (2023 ACC/AHA/ACCP/HRS AF guideline, COR 1). Heart rate control is also reasonable in rheumatic mitral stenosis with AF and a rapid ventricular response (2020 ACC/AHA valvular heart disease guideline, COR 2a).
She can tolerate IV beta-blockade because her blood pressure is preserved (118/76 mm Hg), she is perfusing well (alert, warm extremities), her oxygenation responds to supplemental oxygen, and her LVEF is 60%. A normal blood pressure alone would not establish this. LV systolic function is usually preserved in mitral stenosis because the obstruction lies upstream of the LV.
An IV loop diuretic is appropriate concurrent therapy for her congestion. It lowers left atrial pressure by reducing volume, but it does not slow the ventricular rate or lengthen diastole, so it does not correct the rate-driven cause.
Why the others are wrong
Intravenous adenosine — Adenosine blocks the AV node for only seconds because its half-life is very short. It does not convert atrial fibrillation to sinus rhythm; it only transiently slows the ventricular response. The rate returns to about 145/min almost at once, so diastolic filling time is never restored. Adenosine terminates reentrant SVTs whose circuit runs through the AV node; AF arises in the atria and does not need the AV node to continue (the trap is applying the SVT algorithm to atrial fibrillation).
Percutaneous mitral balloon commissurotomy — This is the definitive treatment for symptomatic severe mitral stenosis with suitable valve anatomy, but it is an elective or semi-elective procedure that does not address this acute decompensation in real time.
Surgical mitral valve replacement — Reserved for severe disease unsuitable for balloon valvuloplasty or with significant mitral regurgitation; not an emergency intervention for acute rate-driven pulmonary edema.
Intravenous amiodarone — it does slow AV-nodal conduction and is tempting in a patient in pulmonary edema, but IV amiodarone is not a preferred rate-control agent; it is reserved for when beta blockers and non-dihydropyridine calcium channel blockers are ineffective or contraindicated, and it can chemically cardiovert a patient with rheumatic mitral stenosis who is not yet anticoagulated (the trap is reaching for the antiarrhythmic first).
Additional high-yield points
Initial stabilization happens in parallel: supplemental oxygen (noninvasive ventilation if hypoxemia persists), IV rate control, an IV loop diuretic for congestion, and anticoagulation. Valvular intervention is considered only once she is stable.
Immediate synchronized cardioversion is indicated for hemodynamic instability attributable to AF (2023 AF guideline, COR 1). Instability means hypotension or shock, ongoing ischemia, altered mentation, or pulmonary edema that worsens or does not respond despite rate control. The valvular guideline adds that cardioversion may be needed if the rate cannot be controlled with medications.
IV diltiazem is an equally recommended alternative when LVEF is >40%, as it is here. IV non-dihydropyridine calcium channel blockers are Class 3: Harm in known moderate or severe LV systolic dysfunction.
IV amiodarone is not a preferred rate-control agent. It is reserved for patients in whom beta blockers and non-dihydropyridine calcium channel blockers are ineffective or contraindicated (2023 AF guideline: COR 2b for critically ill or decompensated heart failure patients in the acute rate-control section, COR 2a in the section on AF with heart failure).
Anticoagulate: rheumatic mitral stenosis with AF calls for a vitamin K antagonist (2020 valvular guideline, COR 1), typically heparin acutely, then warfarin. Warfarin is recommended over DOACs in this setting (2023 AF guideline).
A mitral valve area of 1.5 cm2 or less defines severe stenosis. Once she is stable, she should be evaluated for PMBC. TEE comes first to exclude left atrial thrombus and more than mild mitral regurgitation, and surgery is reserved for patients who are not PMBC candidates.
That's 2. Get 7,700+ more.
Unlock the full FirstPassPA bank: 7,700+ board-style questions, flashcards, and an AI tutor that explains every answer. Your 7-day free trial includes everything, and there's no credit card required.
You've read your 2 free diagnosis previews. Create your free account to unlock the full Mitral Stenosis (MS) outline — plus all 514 diagnoses, 7,700+ board-style questions, flashcards, and an AI tutor. Your 7-day free trial includes everything, and there's no credit card required.
Prior rheumatic fever after untreated group A strep pharyngitis
Living in or migrating from areas with endemic rheumatic disease
Mitral annular calcification (degenerative MS in elderly)
Radiation therapy to the chest
Carcinoid heart disease, SLE (Libman-Sacks), congenital MS
Pathophysiology
Rheumatic inflammation causes commissural fusion, leaflet thickening, and chordal shortening — producing a fish-mouth or funnel-shaped orifice. Obstruction raises left atrial pressure, leading to LA enlargement, pulmonary venous congestion, and eventually pulmonary arterial hypertension and right heart failure. The LV itself is typically protected.
Low-pitched mid-diastolic rumble with presystolic accentuation, best heard at apex in left lateral decubitus with bell
Shorter A2-OS interval indicates more severe stenosis
Right heart failure signs: elevated JVP, peripheral edema, hepatomegaly
Mitral facies — pinkish-purple cheek discoloration in advanced disease
Loud P2 with pulmonary hypertension
Differential diagnosis
Left atrial myxoma — Positional dyspnea, tumor plop instead of opening snap, embolic events; echo shows mobile LA mass
Cor triatriatum — Congenital fibromuscular membrane dividing LA; presents in childhood with MS-like physiology
Severe mitral annular calcification — Degenerative cause in elderly; echo shows annular Ca²⁺ without commissural fusion
Mitral regurgitation — Holosystolic, not diastolic; volume-overload LV instead of pressure-loaded LA only
Pulmonary hypertension of other cause — Right-sided signs without diastolic rumble or opening snap
Austin Flint murmur of AR — Diastolic rumble at apex but with decrescendo diastolic AR murmur and wide pulse pressure; no opening snap
Diagnostic workup
Diagnostic criteria
Severe MS: mitral valve area ≤1.5 cm² (very severe ≤1.0), mean transmitral gradient >5-10 mmHg at heart rate 60-80, resting pulmonary artery systolic pressure >50 mmHg.
Labs
CBC, BMP, TSH (Afib workup)
BNP, troponin if dyspnea acute
Anti-streptolysin O if history unclear
Imaging
Transthoracic echo — diagnostic; planimetry of mitral valve area, mean gradient, pulmonary artery pressure, Wilkins score for valvuloplasty candidacy
Transesophageal echo to exclude LA appendage thrombus before percutaneous mitral balloon valvuloplasty (PMBV) or cardioversion
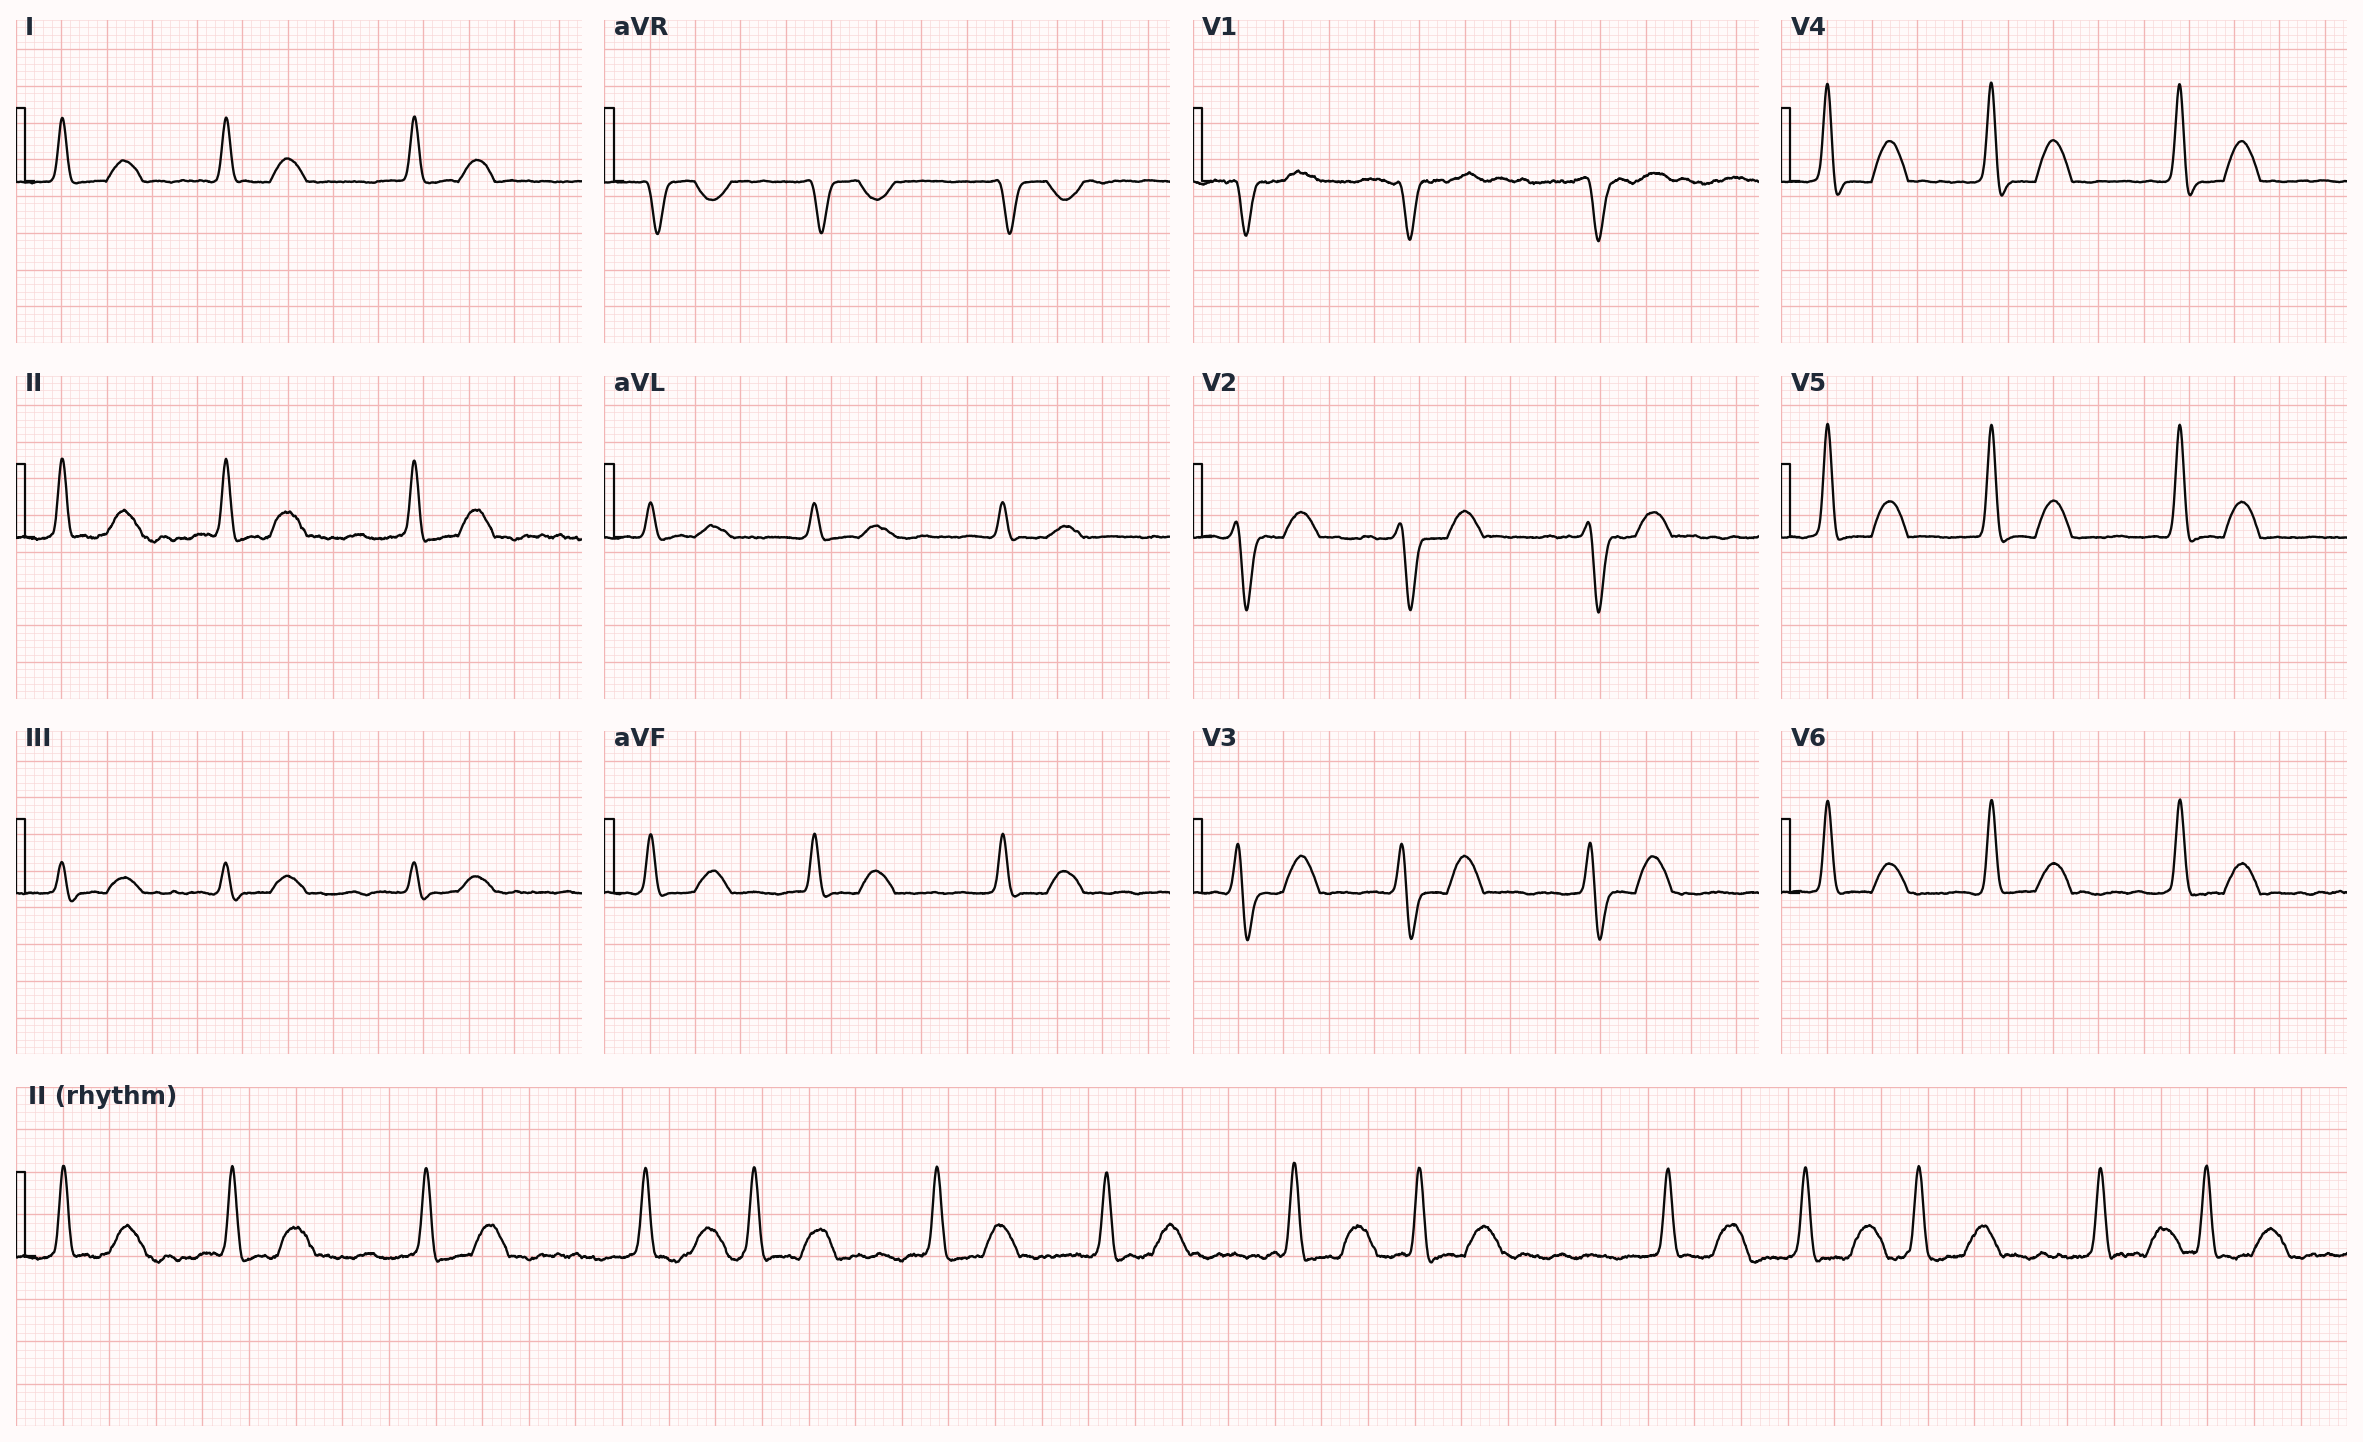
ECG: P mitrale (broad notched P in lead II), atrial fibrillation, right axis deviation, RVH
CXR: straightened left heart border (LA enlargement), Kerley B lines, double density at right heart border, elevated left mainstem bronchus
Diagnostic algorithm
flowchart TD
  A[Symptomatic MS<br/>MVA ≤1.5 cm²] --> B[Transesophageal echo<br/>Wilkins score, LA thrombus?]
  B --> C{Favorable anatomy<br/>Wilkins ≤8?<br/>No thrombus, no MR?}
  C -->|Yes| D[Percutaneous mitral<br/>balloon valvuloplasty]
  C -->|No| E[Surgical mitral<br/>valve replacement]
  D --> F[Lifelong rheumatic<br/>prophylaxis if indicated]
  E --> F
  A --> G[Concurrent: diuretic,<br/>rate control,<br/>WARFARIN if Afib]
Decision pathway for severe symptomatic mitral stenosis.
Treatment
First-line
Diuretics (furosemide, torsemide) for pulmonary and systemic congestion
Rate control for Afib: beta-blocker (metoprolol, bisoprolol) or non-dihydropyridine CCB (diltiazem, verapamil) to lengthen diastolic filling time
Anticoagulation with WARFARIN (target INR 2-3) for Afib, prior embolism, or LA thrombus — DOACs are CONTRAINDICATED in rheumatic MS
Secondary rheumatic fever prophylaxis with IM benzathine penicillin G every 3-4 weeks for at-risk patients
Second-line / adjunct
Percutaneous mitral balloon valvuloplasty (PMBV) — preferred when symptomatic severe MS with favorable valve morphology (low Wilkins score ≤8, no significant MR, no LA thrombus)
Surgical mitral valve repair or replacement (mechanical or bioprosthetic) — for unfavorable anatomy, concomitant valve disease, or failed PMBV
Bioprosthetic valve preferred in older patients; mechanical in younger patients willing to take lifelong warfarin
Complications
Atrial fibrillation and systemic embolism (especially stroke)
Pulmonary hypertension and right heart failure
Infective endocarditis
Hemoptysis
Recurrent rheumatic activity
PANCE pearls
DOACs (apixaban, rivaroxaban, dabigatran) are NOT used in rheumatic MS — use warfarin only.
Pregnancy unmasks MS: increased blood volume and HR shorten diastole, raising LA pressure dramatically.
A shorter A2-OS interval suggests more severe stenosis (higher LA pressure opens the valve sooner).
Ortner syndrome — hoarseness from giant LA compressing the recurrent laryngeal nerve.
PMBV requires absence of LA thrombus on TEE and low Wilkins score; otherwise pursue surgery.
Images
Atrial fibrillation — irregularly irregular rhythm with no organized P waves; left atrial enlargement makes it the most common arrhythmia in mitral stenosis, and it raises the risk of systemic embolism
References
ACC/AHA 2020 VHD — 2020 ACC/AHA Guideline for the Management of Patients with Valvular Heart Disease (Otto et al., Circulation 2021)
ESC/EACTS 2025 — 2025 ESC/EACTS Guidelines for the management of valvular heart disease (Praz et al., Eur Heart J 2025;46:4635-4736)
INVICTUS Trial — Rivaroxaban in Rheumatic Heart Disease–Associated Atrial Fibrillation (Connolly et al., N Engl J Med 2022;387:978-988)
Practice Cardiovascular questions on FirstPassPA
Turn this outline into retention. 7,700+ board-style questions with an AI tutor that explains every answer — free to start, no card required.
Educational use only. This outline is a study aid for PA students and is not medical advice or a substitute for clinical judgment. FirstPassPA is an independent study tool and is not affiliated with, endorsed by, or sponsored by NCCPA or PAEA. PANCE® and PANRE® are registered trademarks of the National Commission on Certification of Physician Assistants; End of Rotation™ is a program of the Physician Assistant Education Association.