Genetic LVH (often asymmetric septal) with dynamic LVOT obstruction — leading cause of SCD in young athletes.
Also known as: HCM, hypertrophic cardiomyopathy, HOCM, IHSS, asymmetric septal hypertrophy
Overview
Primary myocardial disease defined by unexplained left ventricular hypertrophy (wall thickness ≥15 mm, or ≥13 mm with family history) in the absence of another cardiac or systemic cause. Often features dynamic left ventricular outflow tract obstruction from systolic anterior motion (SAM) of the mitral valve.
Epidemiology
Prevalence ~1 in 500. Autosomal dominant inheritance in most familial cases. Most common cause of sudden cardiac death in young athletes in the US.
Try two board-style Hypertrophic Cardiomyopathy questions
Real questions from the FirstPassPA bank, with the full explanation. Pick an answer — no signup, no email.
Question 1CardiovascularEasy
A 35-year-old competitive athlete reports exertional lightheadedness. Cardiac examination reveals a harsh crescendo-decrescendo systolic murmur best heard at the left lower sternal border that does not radiate to the carotids. Which of the following maneuvers is most likely to increase the intensity of this murmur?
ASquatting
BDeep inspiration
CPassive leg raise
DValsalva maneuver
ESustained handgrip
Reveal answer & full explanation
Correct answer: D — Valsalva maneuver
ASquatting
BDeep inspiration
CPassive leg raise
DValsalva maneuver✓
ESustained handgrip
Why Valsalva maneuver is correct
A harsh systolic murmur at the left lower sternal border that does not radiate to the carotids in a young athlete with exertional symptoms is characteristic of hypertrophic obstructive cardiomyopathy.
The murmur arises from dynamic left ventricular outflow tract obstruction, which worsens when the ventricle is smaller.
The Valsalva strain phase decreases preload and left ventricular volume, increasing the outflow gradient and intensifying the murmur.
Why the others are wrong
Squatting — increases preload and afterload, enlarging the ventricle and widening the outflow tract, which softens the murmur (opposite-direction trap).
Passive leg raise — augments venous return and preload, increasing ventricular volume and reducing the gradient (opposite-direction trap).
Sustained handgrip — raises afterload, which increases ventricular volume and decreases the dynamic obstruction, softening the murmur (confused-with-regurgitant-murmur trap: handgrip intensifies the murmurs of mitral regurgitation, aortic regurgitation and ventricular septal defect).
Deep inspiration — inspiration increases venous return to the right heart and augments right-sided murmurs such as tricuspid regurgitation at the left lower sternal border, but it is not a maneuver that intensifies the dynamic left ventricular outflow obstruction of hypertrophic obstructive cardiomyopathy (the trap is assigning a left lower sternal border murmur to the right heart).
Question 2CardiovascularEasy
A 19-year-old college athlete collapses during a basketball game and is successfully defibrillated. ECG shows left ventricular hypertrophy by voltage criteria with deep, narrow Q waves in the inferior and lateral leads, and echocardiography shows asymmetric septal hypertrophy with a 22-mm septum and systolic anterior motion of the mitral valve. Genetic testing identifies a mutation in MYH7. Which protein is encoded by this gene?
ABeta-myosin heavy chain
BCardiac troponin T
CCardiac alpha-actin
DAlpha-myosin heavy chain
ECardiac myosin-binding protein C
Reveal answer & full explanation
Correct answer: A — Beta-myosin heavy chain
ABeta-myosin heavy chain✓
BCardiac troponin T
CCardiac alpha-actin
DAlpha-myosin heavy chain
ECardiac myosin-binding protein C
Why beta-myosin heavy chain is correct
Hypertrophic cardiomyopathy (HCM) is the most common monogenic cardiovascular disorder and is caused by mutations in sarcomeric protein genes.
MYH7 encodes the beta-myosin heavy chain — historically the first HCM gene identified and one of the two most commonly mutated, alongside MYBPC3 (myosin-binding protein C).
HCM is fundamentally a 'disease of the sarcomere.'
Why the others are wrong
Cardiac myosin-binding protein C — Cardiac myosin-binding protein C is encoded by MYBPC3, not MYH7.
Cardiac alpha-actin — Cardiac alpha-actin is encoded by ACTC1.
Cardiac troponin T — Cardiac troponin T is encoded by TNNT2.
Alpha-myosin heavy chain — the two cardiac myosin heavy-chain genes sit side by side on chromosome 14 and are easy to swap, but alpha-myosin heavy chain is encoded by MYH6 and is the minor isoform in the adult human ventricle; MYH7 encodes the beta isoform that predominates there.
That's 2. Get 7,700+ more.
Unlock the full FirstPassPA bank: 7,700+ board-style questions, flashcards, and an AI tutor that explains every answer. Your 7-day free trial includes everything, and there's no credit card required.
You've read your 2 free diagnosis previews. Create your free account to unlock the full Hypertrophic Cardiomyopathy (HCM) outline — plus all 514 diagnoses, 7,700+ board-style questions, flashcards, and an AI tutor. Your 7-day free trial includes everything, and there's no credit card required.
Sarcomere mutations produce myocyte hypertrophy, disarray, and interstitial fibrosis. Asymmetric septal hypertrophy narrows the LVOT, and during systole the anterior mitral leaflet is pulled into the septum (SAM), creating dynamic obstruction and posteriorly-directed mitral regurgitation. Diastolic dysfunction is universal. The disorganized myocardium serves as a substrate for ventricular arrhythmia.
Clinical presentation
Symptoms
Often asymptomatic; HCM detected on screening or after sudden death of a family member
Sudden cardiac death may be the first manifestation
Signs / physical exam
Brisk, bisferiens carotid pulse (spike-and-dome)
Sustained, displaced apical impulse with palpable presystolic component (S4)
Harsh systolic ejection murmur at LLSB — INCREASES with Valsalva strain and standing (decreased preload), DECREASES with squatting or handgrip (increased afterload/preload)
Holosystolic apical murmur of MR from SAM
S4 gallop from forceful atrial contraction into stiff LV
Differential diagnosis
Aortic stenosis — Fixed obstruction — murmur DECREASES with Valsalva; calcified valve on echo
Athlete's heart — Symmetric hypertrophy ≤13 mm, regresses with detraining, normal diastolic function, larger LV cavity
Hypertensive LVH — Symmetric concentric LVH in patient with chronic HTN; usually wall thickness <15 mm
Cardiac amyloidosis — Thickened walls but LOW voltage on ECG, granular sparkling myocardium, pseudo-Q waves; confirm with PYP scan or biopsy
Mitral valve prolapse — Mid-systolic click; murmur shifts with Valsalva but no LVH
Diagnostic workup
Diagnostic criteria
Adult: maximum LV wall thickness ≥15 mm unexplained by loading conditions, or ≥13 mm with affected family member or positive genetic testing. Obstructive HCM = peak LVOT gradient ≥30 mmHg at rest or with provocation (Valsalva, standing, exercise); ≥50 mmHg is hemodynamically significant and is the threshold for septal reduction therapy in symptomatic patients.
Labs
Basic labs; consider genetic testing in proband and cascade screen of first-degree relatives
BNP/NT-proBNP for severity assessment
Cardiac enzymes if chest pain
Imaging
Transthoracic echo — diagnostic; document septal thickness, LVOT gradient at rest and with provocation (Valsalva, exercise), SAM, MR
Cardiac MRI with late gadolinium enhancement — extent of fibrosis and SCD risk stratification, mass quantification, apical HCM identification
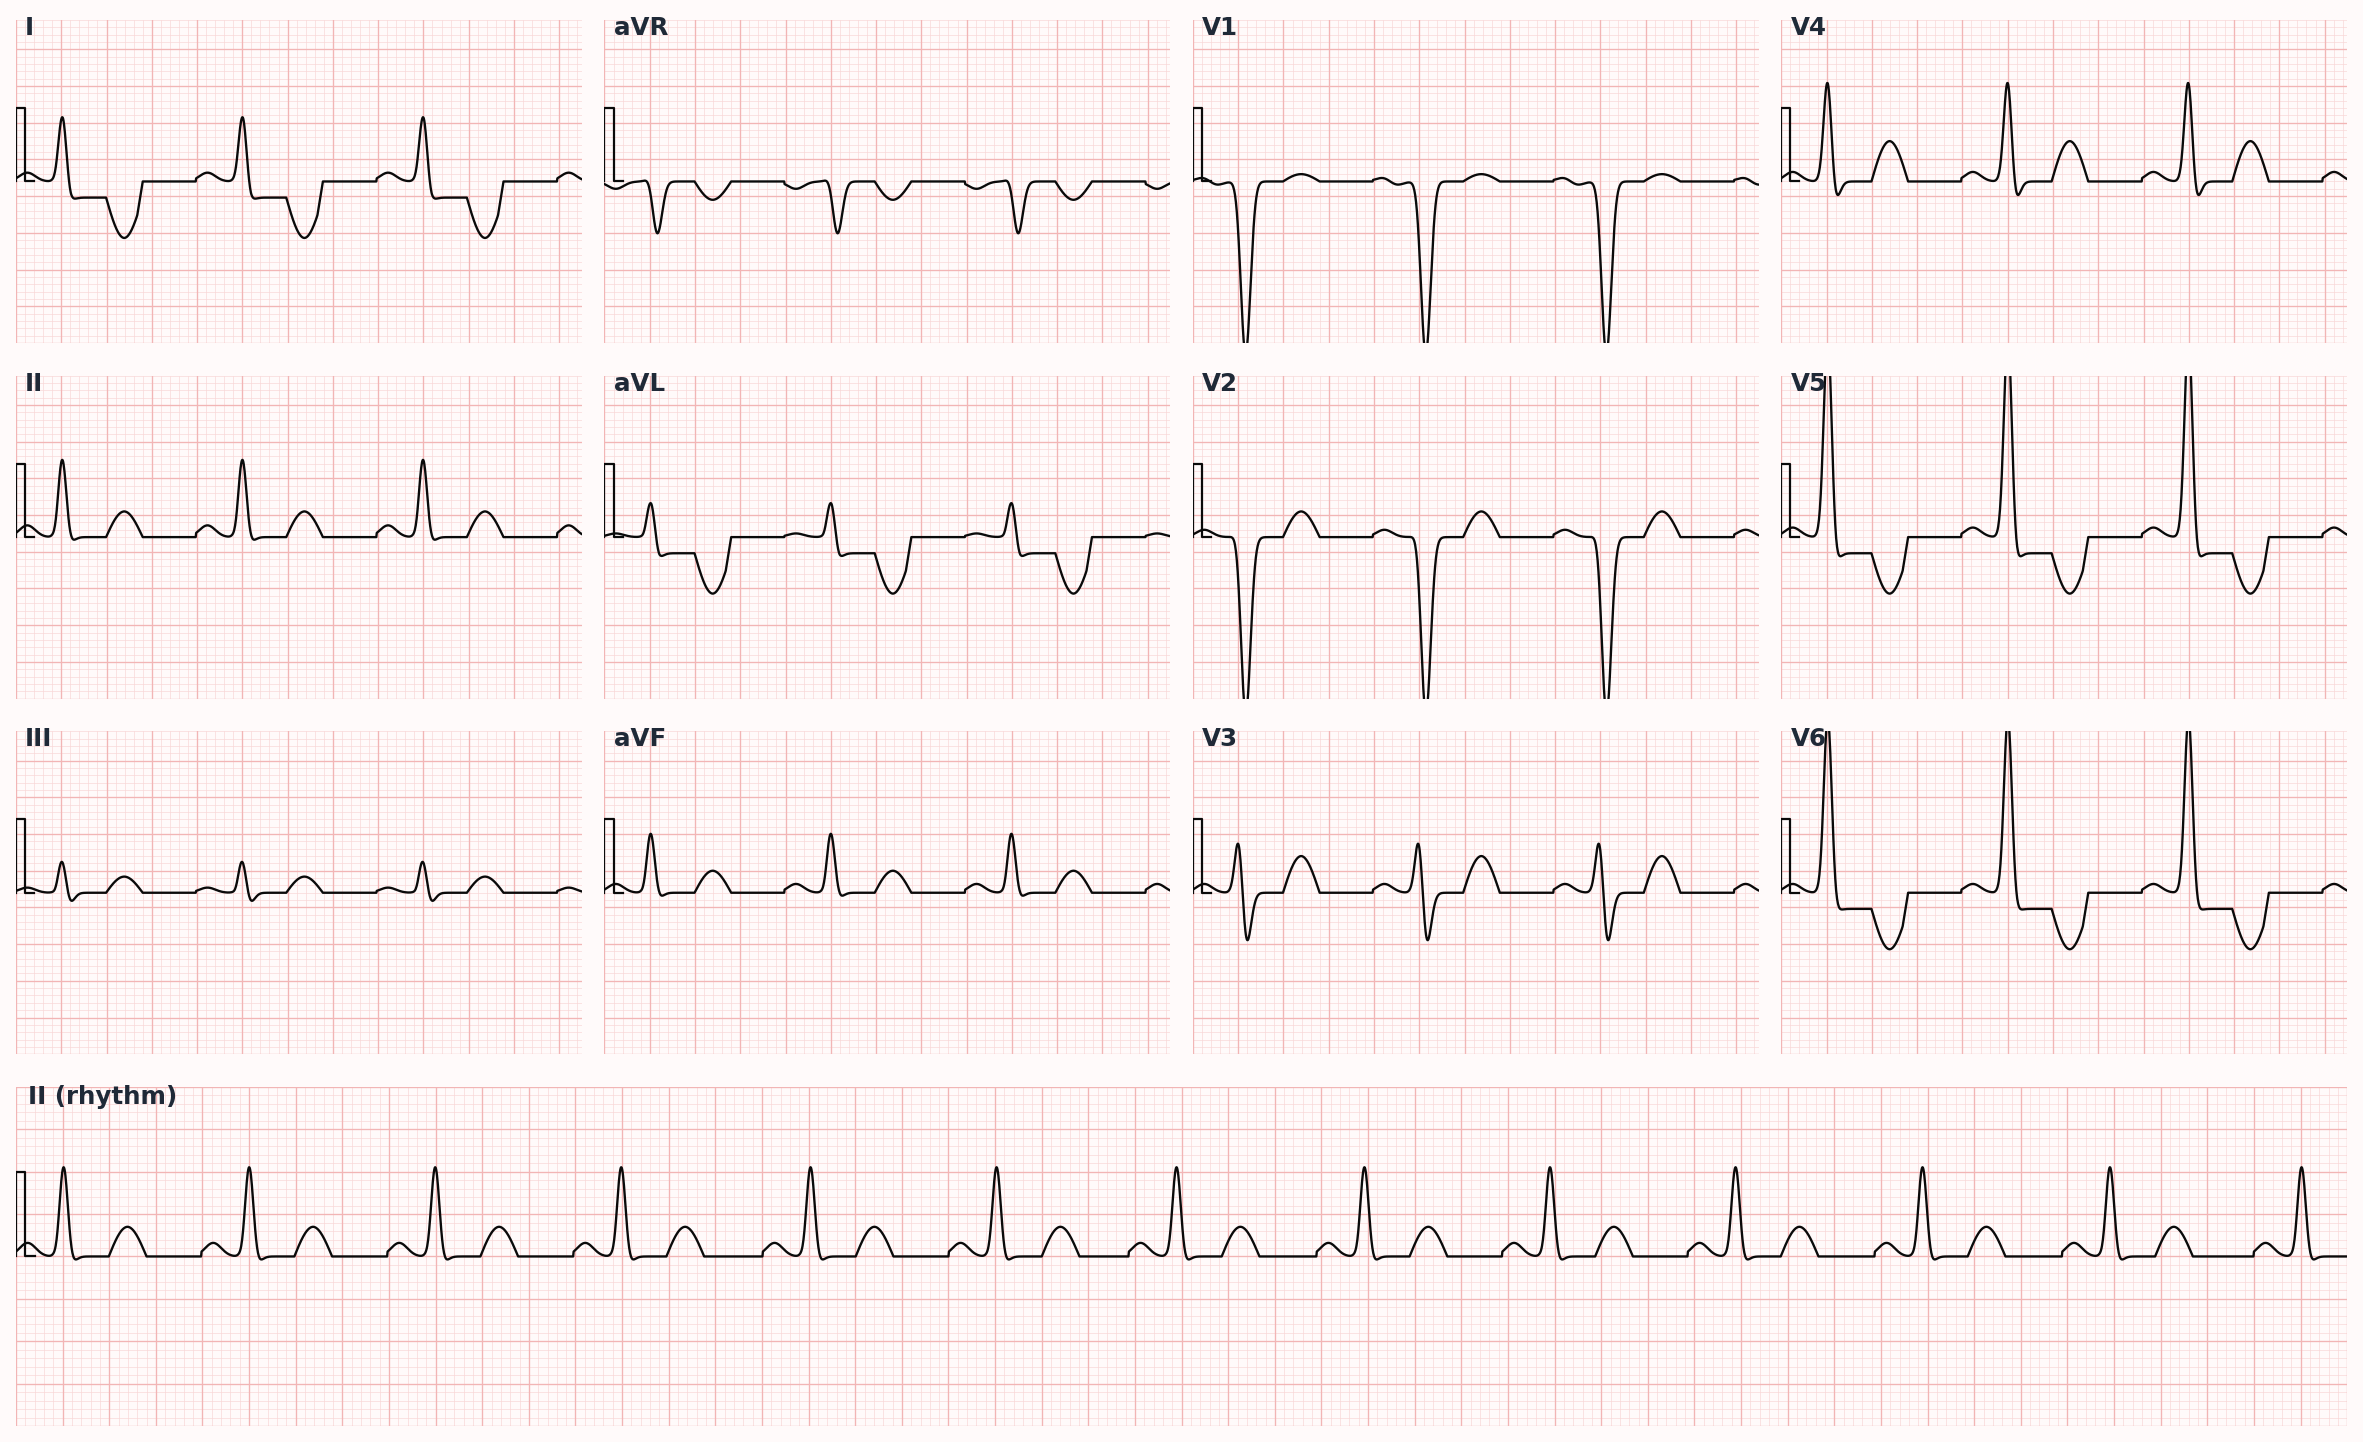
ECG — LVH with strain, deep narrow Q waves (septal hypertrophy), giant precordial T-wave inversions in apical HCM (Yamaguchi)
Holter monitor — screen for non-sustained VT (SCD risk factor)
Exercise stress echo to provoke LVOT gradient
Diagnostic algorithm
Maneuver
Preload / Afterload
HCM murmur
Aortic stenosis murmur
MVP click-murmur
Valsalva (strain)
↓ Preload
LOUDER
Softer
Click earlier, murmur longer
Standing from squat
↓ Preload
LOUDER
Softer
Click earlier, murmur longer
Squatting
↑ Preload, ↑ Afterload
Softer
Louder
Click later, murmur shorter
Sustained handgrip
↑ Afterload
Softer
Softer
Click later, murmur louder if MR
Passive leg raise
↑ Preload
Softer
Louder
Click later, murmur shorter
Bedside maneuvers help distinguish HCM from AS and MVP.
Treatment
First-line
Avoid dehydration, excess alcohol, and sudden standing; mild-to-moderate exercise is encouraged, and vigorous or competitive sports are decided by shared decision-making with an HCM expert rather than blanket disqualification (2024 AHA/ACC)
Symptomatic obstructive HCM: non-vasodilating beta-blocker (metoprolol, atenolol, propranolol) titrated to symptoms and HR
Non-dihydropyridine CCB (verapamil, diltiazem) if beta-blocker not tolerated
AVOID: dihydropyridine CCBs, ACEi/ARBs, digoxin, nitrates, and aggressive diuresis in obstructive HCM (worsen gradient); low-dose diuretics may be used cautiously for persistent congestion
Disopyramide added for refractory symptoms (negative inotrope)
Septal reduction therapy — surgical septal myectomy (preferred in young patients, experienced center) or alcohol septal ablation — for refractory symptoms with LVOT gradient ≥50 mmHg despite optimal medical therapy
ICD placement — Class I for survivors of cardiac arrest or sustained VT; Class IIa for ≥1 major risk factor (HCM-related sudden death in a first-degree or close relative ≤50 years, unexplained presumed-arrhythmic syncope, LV wall thickness ≥30 mm, LV apical aneurysm, LVEF <50%; in children, NSVT also counts); in adults, NSVT on Holter or extensive LGE on MRI (≥15% of LV mass) may be considered only when the decision is otherwise uncertain (Class IIb); abnormal BP response to exercise is no longer used
Family screening — first-degree relatives by ECG and echo every 1-2 years in children and adolescents (every 2-3 years if lower risk) and every 3-5 years in adults; genetic testing if a pathogenic variant is identified in proband
Heart transplant for end-stage HCM with refractory heart failure
Complications
Sudden cardiac death (annual risk ~1% overall, higher in those with risk factors)
Atrial fibrillation with embolic stroke
Heart failure (obstructive and end-stage burnout/dilated phase)
Infective endocarditis (rare)
Conduction disease after septal ablation/myectomy
PANCE pearls
HCM murmur INCREASES with Valsalva or standing (decreased preload) — opposite of most systolic murmurs.
Mavacamten (EXPLORER-HCM) reduces LVOT gradient and improves symptoms in obstructive HCM.
First-degree relatives need cascade screening — even asymptomatic carriers may carry SCD risk.
Avoid dihydropyridine CCBs (nifedipine, amlodipine), ACE inhibitors, nitrates, and digoxin in obstructive HCM — they worsen LVOT gradient.
Apical (Yamaguchi) HCM: giant precordial T-wave inversions and spade-shaped LV cavity on echo/MRI — Japanese predominance, generally favorable prognosis.
Atrial fibrillation in HCM (clinical, or device-detected lasting >24 h) warrants anticoagulation regardless of CHA2DS2-VASc score, with a DOAC first-line.
Images
Left ventricular hypertrophy with strain — tall precordial voltage with lateral ST depression and T-wave inversion; HCM can also show deep, narrow Q waves in the inferior and lateral leads (not shown here)
References
AHA/ACC 2024 HCM — 2024 AHA/ACC/AMSSM/HRS/PACES/SCMR Guideline for the Management of Hypertrophic Cardiomyopathy (Ommen SR et al., Circulation 2024;149:e1239-e1311)
ESC 2023 HCM — 2023 ESC Guidelines for the Management of Cardiomyopathies (Arbelo et al., Eur Heart J 2023)
EXPLORER-HCM — Mavacamten for Treatment of Symptomatic Obstructive HCM (Olivotto et al., Lancet 2020)
VALOR-HCM — Myosin Inhibition in Patients With Obstructive Hypertrophic Cardiomyopathy Referred for Septal Reduction Therapy (Desai et al., JACC 2022)
Practice Cardiovascular questions on FirstPassPA
Turn this outline into retention. 7,700+ board-style questions with an AI tutor that explains every answer — free to start, no card required.
Educational use only. This outline is a study aid for PA students and is not medical advice or a substitute for clinical judgment. FirstPassPA is an independent study tool and is not affiliated with, endorsed by, or sponsored by NCCPA or PAEA. PANCE® and PANRE® are registered trademarks of the National Commission on Certification of Physician Assistants; End of Rotation™ is a program of the Physician Assistant Education Association.