Magnesium disorders from GI loss, diuretics, alcoholism (low), or renal failure and iatrogenic infusion (high).
Also known as: hypomagnesemia, hypermagnesemia, magnesium deficiency, low magnesium, high magnesium
Overview
Hypomagnesemia is serum magnesium <1.7 mg/dL (severe <1.0 mg/dL). Hypermagnesemia is >2.6 mg/dL (symptoms usually appear >4.8 mg/dL; severe >7 mg/dL). Magnesium is the second most abundant intracellular cation. Homeostasis depends on intestinal absorption (~30-40% of intake) and renal handling: 70% reabsorbed in the thick ascending limb via paracellular transport (claudin-16/19) and 10% in the distal convoluted tubule (TRPM6).
Epidemiology
Hypomagnesemia is common: present in up to 12% of hospitalized patients and 60% of ICU patients. Hypermagnesemia is rare outside of obstetric magnesium therapy (preeclampsia/eclampsia), renal failure with magnesium-containing laxatives/antacids, or massive overdose.
Try two board-style Hypomagnesemia and Hypermagnesemia questions
Real questions from the FirstPassPA bank, with the full explanation. Pick an answer — no signup, no email.
Question 1RenalMedium
A 58-year-old man with type 2 diabetes is hospitalized for cellulitis. On hospital day 3 he develops muscle cramps and a fine tremor. Serum magnesium is 1.2 mg/dL (reference 1.7-2.6) and serum potassium is 3.0 mEq/L despite repeated potassium replacement. He takes hydrochlorothiazide for hypertension and has normal renal function. Spot urine magnesium and creatinine levels are obtained. Which of the following findings best supports a renal cause of his hypomagnesemia?
AFractional excretion of magnesium of 6%
BFractional excretion of sodium of 3%
CFractional excretion of magnesium of 1%
DSerum potassium near 3.0 mEq/L on labs
EProlonged QT interval on the resting ECG
Reveal answer & full explanation
Correct answer: A — Fractional excretion of magnesium of 6%
AFractional excretion of magnesium of 6%✓
BFractional excretion of sodium of 3%
CFractional excretion of magnesium of 1%
DSerum potassium near 3.0 mEq/L on labs
EProlonged QT interval on the resting ECG
Why Fractional excretion of magnesium of 6% is correct
The kidney normally conserves magnesium avidly when serum levels fall, so a truly hypomagnesemic patient should excrete almost none in the urine.
FEMg = (urine Mg x serum Cr x 100) / (0.7 x serum Mg x urine Cr); a value above 2% during hypomagnesemia signals inappropriate renal wasting rather than extrarenal (GI or dietary) loss.
A FEMg of 6% localizes the loss to the kidney, here the thiazide diuretic. Other renal culprits include loop diuretics, calcineurin inhibitors, EGFR inhibitors, and hereditary tubulopathies such as Gitelman syndrome.
Why the others are wrong
Prolonged QT interval on the resting ECG — this reflects the severity of the deficit and torsades risk, not the site of magnesium loss.
Serum potassium near 3.0 mEq/L on labs — hypokalemia frequently coexists with hypomagnesemia, and potassium repletion is futile until magnesium is replaced (low intracellular Mg removes its normal block on ROMK, so potassium is wasted in the urine), but it does not tell you whether the magnesium loss is renal or extrarenal.
Fractional excretion of magnesium of 1% — a FEMg below 2% during hypomagnesemia means the kidney is appropriately conserving magnesium, which points to extrarenal loss (diarrhea, malabsorption, poor intake, or proton pump inhibitor use) rather than renal wasting.
Fractional excretion of sodium of 3% — FENa is the familiar fractional excretion used to localize acute kidney injury, but it measures sodium handling and is unreliable in a patient taking a thiazide; it says nothing about magnesium, and only urinary magnesium excretion, such as a FEMg above 2% during hypomagnesemia, shows renal magnesium wasting.
Question 2RenalMedium
A 58-year-old man with chronic alcohol use is admitted for weakness. Blood pressure is 124/78 mm Hg. Initial labs show potassium 2.7 mEq/L and magnesium 1.1 mg/dL. He receives 80 mEq of intravenous potassium chloride over several hours, but a repeat potassium remains 2.8 mEq/L. Renal function and acid-base status are normal, and he is not vomiting or having diarrhea. Which of the following best explains his persistent hypokalemia despite potassium repletion?
AImpaired thick ascending limb chloride reabsorption raises distal sodium delivery and potassium loss
BAldosterone excess drives collecting-duct sodium reabsorption coupled to potassium secretion
CMagnesium depletion relieves the block on renal ROMK channels, raising potassium secretion
EInsulin shifts potassium from the extracellular fluid into the intracellular compartment
Why Magnesium depletion relieves the block on renal ROMK channels, raising potassium secretion is correct
Intracellular magnesium normally blocks the renal outer medullary potassium (ROMK) channel in the distal nephron; when magnesium is depleted, the block is lost and ROMK secretes potassium unchecked into the urine.
As long as the patient remains hypomagnesemic, administered potassium is wasted in the urine, producing the classic refractory hypokalemia.
The fix is to replete magnesium first; potassium repletion is futile in untreated hypomagnesemia, which is exactly this patient with a magnesium of 1.1 mg/dL.
Why the others are wrong
Aldosterone excess driving collecting-duct potassium secretion would cause hypokalemia, but this patient is normotensive with normal acid-base status and no clue to hyperaldosteronism, and it would not explain why potassium responds only after magnesium is corrected.
Insulin shifting potassium into cells produces a transient transcellular shift rather than ongoing urinary loss, so total body potassium is unchanged and it does not account for true depletion here.
Impaired thick ascending limb chloride reabsorption is the Bartter or loop-diuretic mechanism; it can cause both hypokalemia and hypomagnesemia but is accompanied by metabolic alkalosis, which is absent in this patient with normal acid-base status and no diuretic exposure.
Impaired distal convoluted tubule NaCl cotransport increases distal sodium delivery and potassium secretion — impaired NCC transport (Gitelman syndrome or a thiazide) is the classic cause of combined hypokalemia and hypomagnesemia with normal blood pressure, which makes it tempting here; but it characteristically produces a hypokalemic metabolic alkalosis, which is absent, nothing suggests thiazide use, and chronic alcohol use readily explains the magnesium depletion that is driving his renal potassium wasting.
That's 2. Get 7,700+ more.
Unlock the full FirstPassPA bank: 7,700+ board-style questions, flashcards, and an AI tutor that explains every answer. Your 7-day free trial includes everything, and there's no credit card required.
You've read your 2 free diagnosis previews. Create your free account to unlock the full Hypomagnesemia and Hypermagnesemia outline — plus all 514 diagnoses, 7,700+ board-style questions, flashcards, and an AI tutor. Your 7-day free trial includes everything, and there's no credit card required.
Hypomagnesemia: alcoholism, chronic diarrhea, malabsorption (celiac, IBD, short bowel, bariatric surgery), proton pump inhibitors (long-term), loop and thiazide diuretics, amphotericin B, aminoglycosides, pentamidine, cisplatin, calcineurin inhibitors (tacrolimus, cyclosporine), cetuximab/panitumumab (EGFR inhibitors), Gitelman and Bartter syndromes, type 2 diabetes
Hypermagnesemia: CKD/ESKD, magnesium-containing antacids (Maalox, milk of magnesia) and laxatives (especially in CKD), obstetric magnesium sulfate therapy, tumor lysis syndrome, lithium toxicity, hypothyroidism, Addison disease
Pathophysiology
Hypomagnesemia: from decreased intake (alcoholism, parenteral nutrition without Mg), decreased absorption (PPIs reduce TRPM6 expression and intestinal Mg uptake), or increased loss — renal (diuretics, calcineurin inhibitors, hereditary tubulopathies) or GI (diarrhea, vomiting). Magnesium is a cofactor for parathyroid hormone secretion and action — severe hypomagnesemia → functional hypoparathyroidism and refractory hypocalcemia. Intracellular Mg normally blocks the ROMK potassium channel in the distal nephron; in hypomagnesemia the block is lost, renal K secretion rises, and KCl repletion is wasted in the urine until Mg is replaced. Hypermagnesemia: almost always from impaired renal excretion combined with an exogenous load (laxative, antacid, infusion). Suppresses neuromuscular transmission, causing weakness and bradyarrhythmias.
Clinical presentation
Symptoms
Hypomagnesemia: tremor, hyperreflexia, muscle cramps, paresthesias, tetany; seizures and ventricular arrhythmias (torsades de pointes) when severe; nausea, weakness, personality changes
Hypermagnesemia: nausea, flushing, headache, lethargy → loss of deep tendon reflexes (~7-10 mg/dL) → respiratory depression (>10) → bradyarrhythmias and cardiac arrest (>12 mg/dL)
Signs / physical exam
Hypomagnesemia: Trousseau and Chvostek signs (from coexisting hypocalcemia), hyperactive reflexes, fasciculations, prolonged QT and U waves on ECG, torsades
Hypermagnesemia: hyporeflexia (early, sensitive), bradycardia, hypotension, prolonged PR and QRS
Classic findings
Refractory hypokalemia and hypocalcemia in a patient with diuretic, alcohol, or PPI use — always replace magnesium first. Loss of patellar reflex in a preeclamptic patient on magnesium sulfate — first sign of toxicity.
Differential diagnosis
Hypocalcemia (other causes) — Hypoparathyroidism, vitamin D deficiency, CKD; check Mg in any refractory hypocalcemia
Hypokalemia (other causes) — Often coexists with hypomagnesemia; cannot fully correct K until Mg replaced (low intracellular Mg removes its normal block on ROMK, so K is wasted in the urine)
Usually not needed; ECG is the key 'imaging' for arrhythmia risk
Diagnostic algorithm
Magnesium level (mg/dL)
Clinical findings
Action
<1.0 (severe low)
Torsades, seizures, tetany
IV MgSO4 1-2 g over 15-60 min; replace before K
1.0-1.7 (mild-mod low)
Cramps, tremor, weakness; refractory hypoK/hypoCa
Oral or IV Mg; identify cause (PPI, diuretic, alcohol)
1.7-2.6 (normal)
—
—
2.6-7.0 (mild-mod high)
Nausea, flushing, lethargy, hyporeflexia
Stop Mg source, IV fluids, loop diuretic
>7.0 (severe high)
Loss of DTRs, hypotension, bradycardia; respiratory depression (>10), cardiac arrest (>12)
IV calcium gluconate, hemodialysis
Magnesium disorder severity and management thresholds.
Treatment
First-line
Hypomagnesemia, mild-moderate, asymptomatic: oral magnesium oxide, magnesium chloride, or magnesium lactate 240-1000 mg elemental Mg/day in divided doses (diarrhea is common dose-limiting effect; sustained-release preparations better tolerated)
Hypomagnesemia, severe or symptomatic (arrhythmia, seizure, tetany): IV magnesium sulfate 1-2 g over 15-60 min (faster if life-threatening), then 4-8 g over 24 hours; for torsades, 1-2 g IV (push if pulseless, over several minutes with a pulse; defibrillate if unstable)
Replace magnesium BEFORE potassium when both are low (potassium repletion is futile in untreated hypomagnesemia)
Identify and treat underlying cause — discontinue offending drug, address malabsorption
Hypermagnesemia, mild-moderate, asymptomatic: discontinue magnesium sources, supportive observation; renal excretion clears Mg if kidney function adequate
Hypermagnesemia, symptomatic or severe: IV calcium gluconate or calcium chloride for cardioprotection (calcium antagonizes Mg at NMJ); IV fluids and loop diuretic (furosemide) to enhance renal excretion; hemodialysis for severe toxicity or anuric patients
Watch for refeeding syndrome with concurrent phosphate, potassium derangement
PPI-associated hypomagnesemia
Trial of stopping PPI or switching to H2 blocker
Oral magnesium replacement; severe cases may need IV courses
Consider amiloride (potassium-sparing diuretic) to increase distal Mg reabsorption
Magnesium sulfate toxicity in obstetrics
Discontinue infusion
IV calcium gluconate 1 g over 5-10 min
Supportive ventilation if respiratory depression
Continuous cardiac monitoring; monitor DTRs as bedside marker
Gitelman / Bartter syndromes
Long-term oral KCl and Mg replacement
Amiloride or spironolactone for potassium and magnesium retention
NSAIDs for Bartter (reduce prostaglandin-driven losses) — cautious use
Second-line / adjunct
Amiloride for chronic refractory renal magnesium wasting
Inulin or pectin-rich diet to improve magnesium absorption (anecdotal)
Burosumab is NOT used for Mg disorders — distinguish from phosphate
Complications
Hypomagnesemia: torsades de pointes and other ventricular arrhythmias, sudden cardiac death, refractory hypokalemia and hypocalcemia, seizures, osteoporosis (long-term), worse outcomes in heart failure and ICU populations
Hypermagnesemia: respiratory failure, cardiac arrest, profound hypotension, ileus, urinary retention; fetal hypotonia and Apgar reduction in neonates of preeclamptic mothers
PANCE pearls
Always check and replete magnesium in refractory hypokalemia or hypocalcemia — potassium cannot be retained without adequate magnesium.
Loss of patellar reflex is the earliest bedside sign of magnesium sulfate toxicity in preeclamptic patients — check reflexes hourly during infusion.
Long-term PPI use is a frequently overlooked cause of hypomagnesemia; FDA labeling warning (Warnings and Precautions, not a boxed warning) since 2011.
IV magnesium sulfate 1-2 g is first-line drug therapy for torsades de pointes regardless of baseline magnesium level (bolus if pulseless, over several minutes if a pulse is present); unstable or pulseless torsades needs immediate unsynchronized defibrillation.
FEMg >2% in a hypomagnesemic patient indicates inappropriate renal wasting and points toward diuretics, calcineurin inhibitors, EGFR inhibitors, or a hereditary tubulopathy.
Images
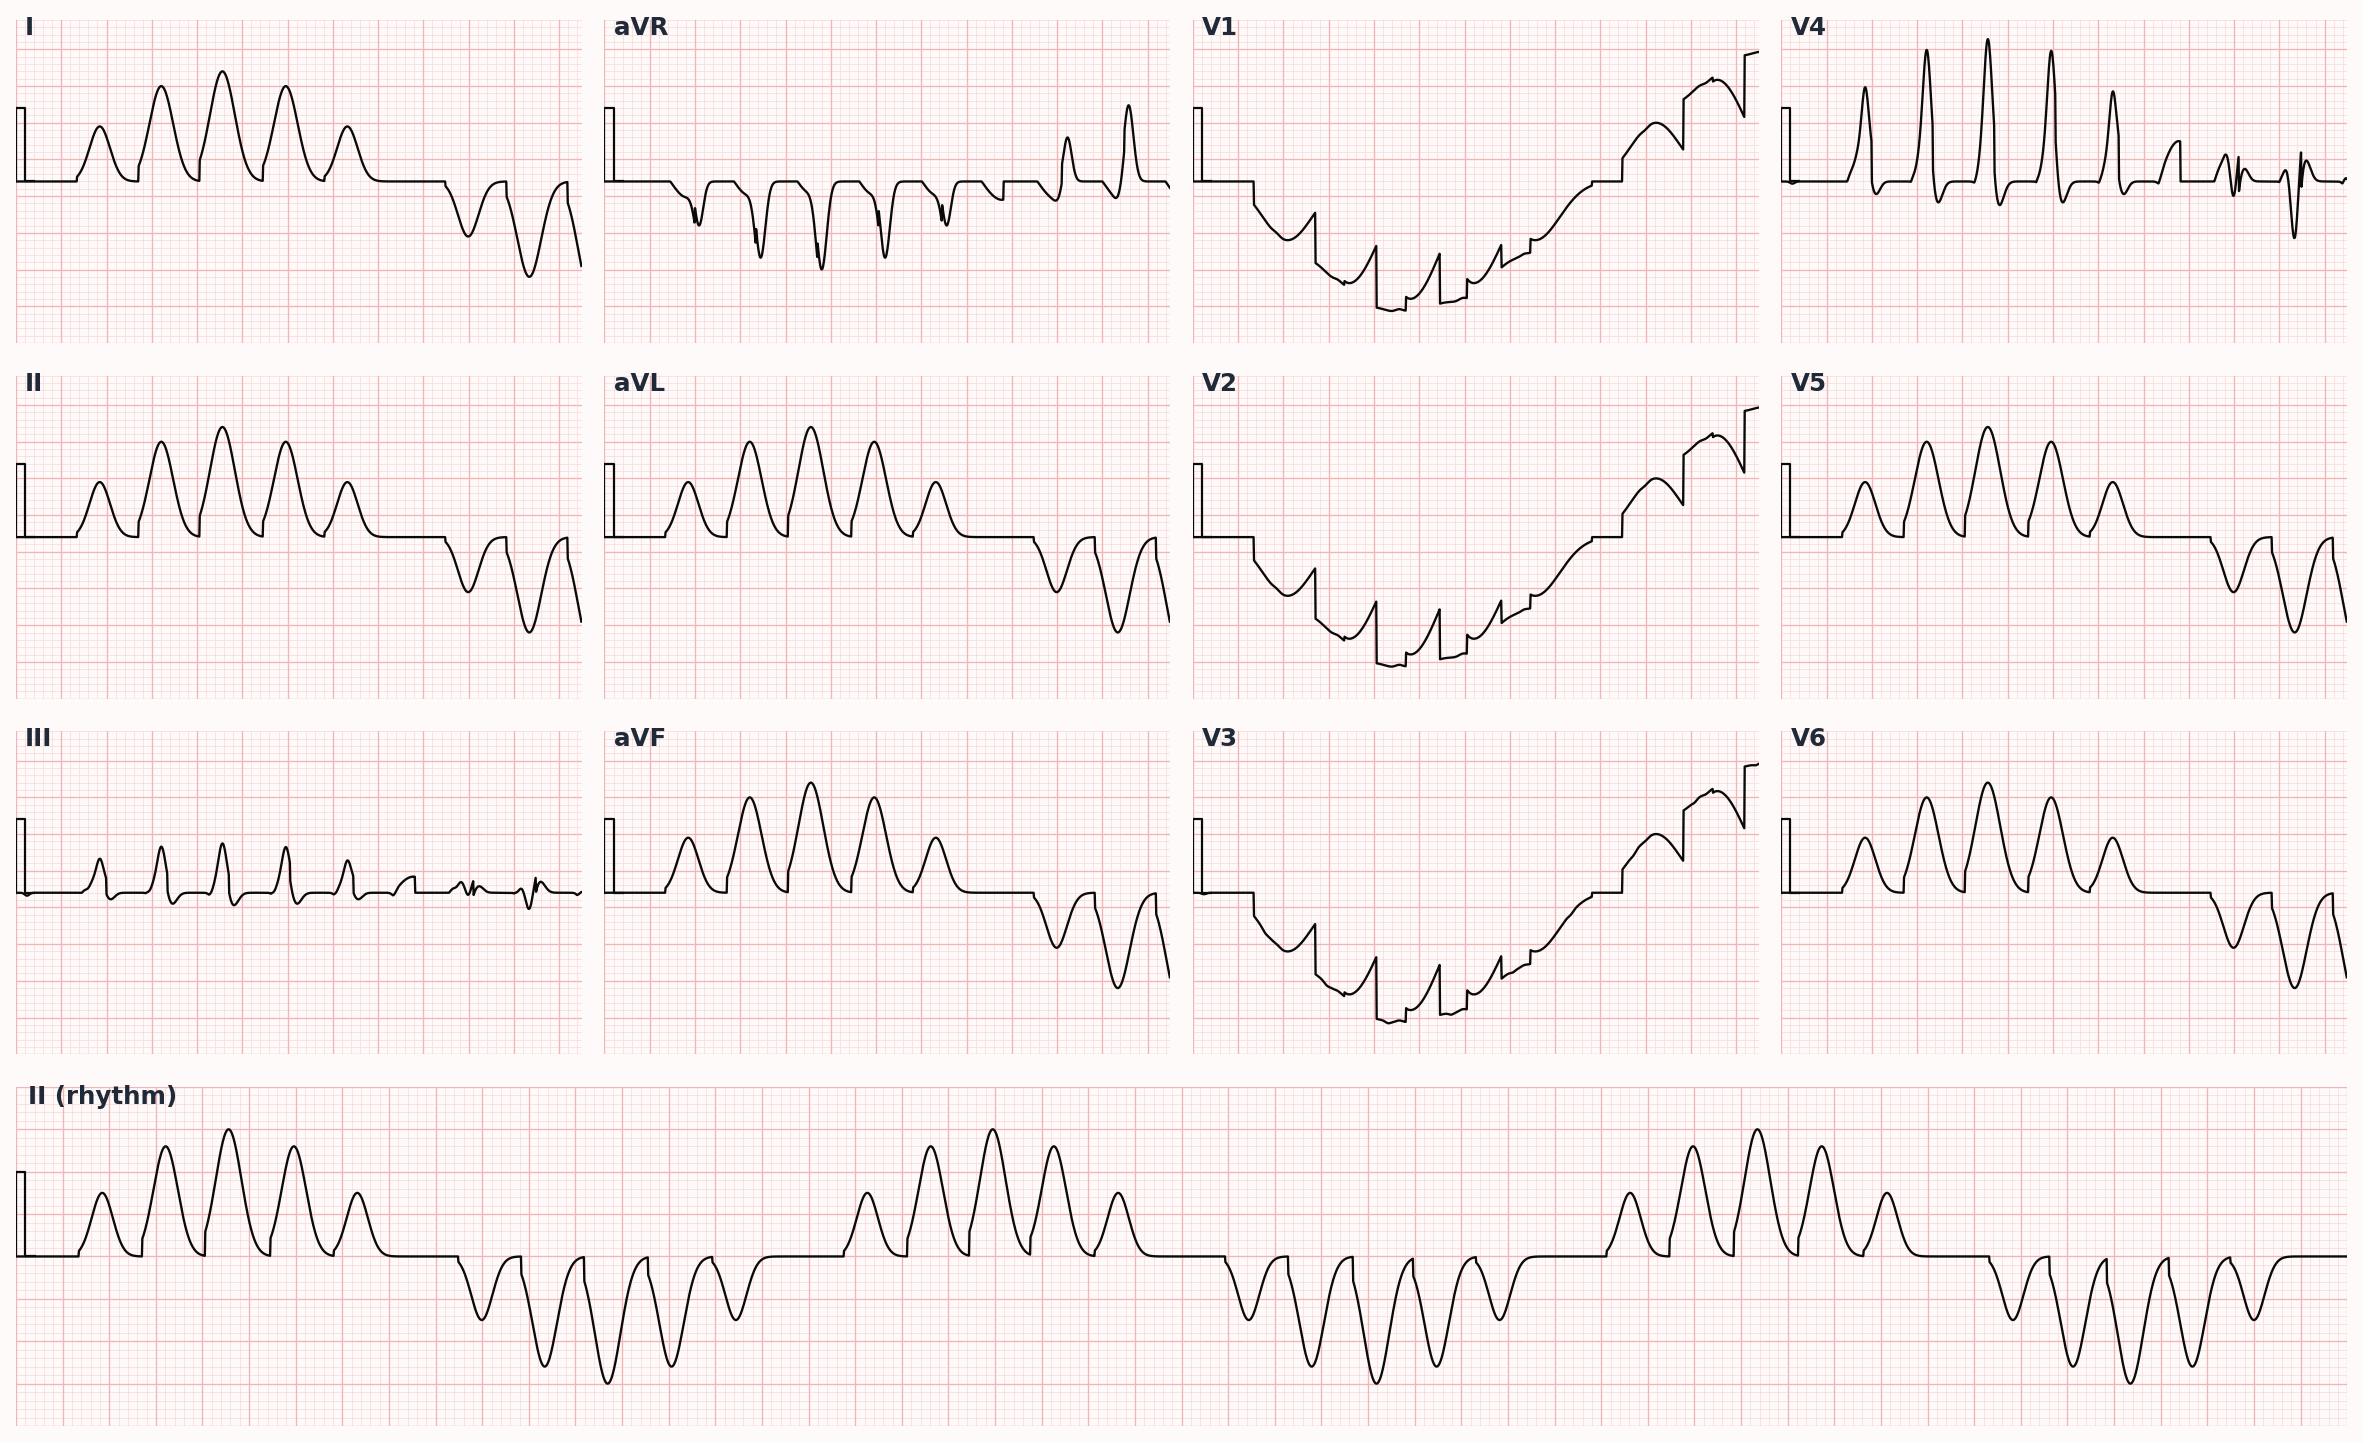
Torsades de pointes — polymorphic ventricular tachycardia with a QRS axis that twists around the baseline; severe hypomagnesemia can trigger it
References
FDA 2011 — FDA Drug Safety Communication: Low magnesium levels can be associated with long-term use of proton pump inhibitor drugs (PPIs) (2011)
ACOG 2020 — ACOG Practice Bulletin No. 222: Gestational Hypertension and Preeclampsia (Obstet Gynecol 2020;135:e237-e260)
Educational use only. This outline is a study aid for PA students and is not medical advice or a substitute for clinical judgment. FirstPassPA is an independent study tool and is not affiliated with, endorsed by, or sponsored by NCCPA or PAEA. PANCE® and PANRE® are registered trademarks of the National Commission on Certification of Physician Assistants; End of Rotation™ is a program of the Physician Assistant Education Association.